3800 words · 20 min read
Biology of optimal dosing
Why can a lower dose prove just as effective?
These notes were originally drafted in 2023 and revised in autumn 2026. I am a biostatistician, not an immunologist, so treat this as only a very basic introduction to a very complex topic.
Basic rationale
There are five groups of factors that determine the vaccine’s effect. The first and most obvious to focus on is the antigen. Then there are (2) the mode of delivery, i.e. how the antigen is “packaged”, but also where it is delivered1, (3) vaccination regimen/schedule, (4) adjuvants, (5) host factors (e.g. age). I will focus on lowering the amount of antigen and then touch on points 2-5 as we go.2
1 This category also includes additional factors such as stabilisation of the structure of the antigen (to make it persist longer) and the number of epitopes (valency), which is beyond my simple understanding of immune responses, so I won’t cover it.
2 I talk a bit about the route of administration in another chapter. It is well-established that using intradermal (ID) delivery may produce comparable immune responses at lower doses than the deeper IM/SC injections. In this section I am talking about an apple-to-apple comparison, i.e. what happens when vaccines are administered using the same route. You can find more examples of increased immunogenicity from switching to ID delivery in case studies, e.g. fractional dosing of polio or mpox vaccines.
That the lower doses are sometimes found to be non-inferior should not be surprising. In vaccine development perspective chapter I discuss the reasons why vaccine makers are incentivised to test high doses. If that feels counter-intuitive to you, you may want to read that first. Here I will try to cover the basics of biological mechanisms. Let’s start by getting a bit more precise about the terms. Let’s talk about response curves and types of response.
What is an immune response to vaccine?
Vaccines mostly induce adaptive immune responses. Within adaptive immunity, we distinguish two mechanisms: humoral and cellular. Humoral is antibody-mediated, involves B cells, plasma cells, and antibodies they produce. T cells do not produce antibodies, but can attack infected cells or help other immune cells; this is cellular immunity.3
Antibodies allow for neutralising pathogens before they enter cells (that could lead to sterilising immunity). They are the key mechanism in vaccination and also easier to measure, hence vaccine developers often focus on them. Typically vaccines rely primarily on antibody-induced protection. Many vaccines also induce a T-cell response; however, it is harder to measure and we understand it less well.
*We should also differentiate between sites of immunity. Typically we will be talking about measurement of antibodies in blood, but for a respiratory infection like Covid or flu mucosal immunity in airways may prevent infection altogether. For oral cholera and polio vaccines intestinal mucosa is the target.
I also talk about correlates of protection in this chapter. That is a marker that statistically * predicts protection against infection/disease. Correlates can be identified with different stringency, as the name implies. Typically we first test a promising vaccine for efficacy and establish CoP’s based on the trial results.
3 First, however, the immune system needs an antigen; the way it is “presented” is specfic to a vaccine platform. E.g. in mRNA cells are instructed to produce antigen. Lipid nanoparticles that mRNA uses play role in both delivery and stimulation of immune system. The relationship between administered dose, antigen exposure and immune response is therefore more complicated.
Immune response vs efficacy; shapes of response
I use the term “response” freely, but in vaccine development we establish two responses: first immunological and then protection from disease. We need to measure both of them to know how a given dose will translate to efficacy. A very simplified scheme looks like this
(I asked AI to generate this):
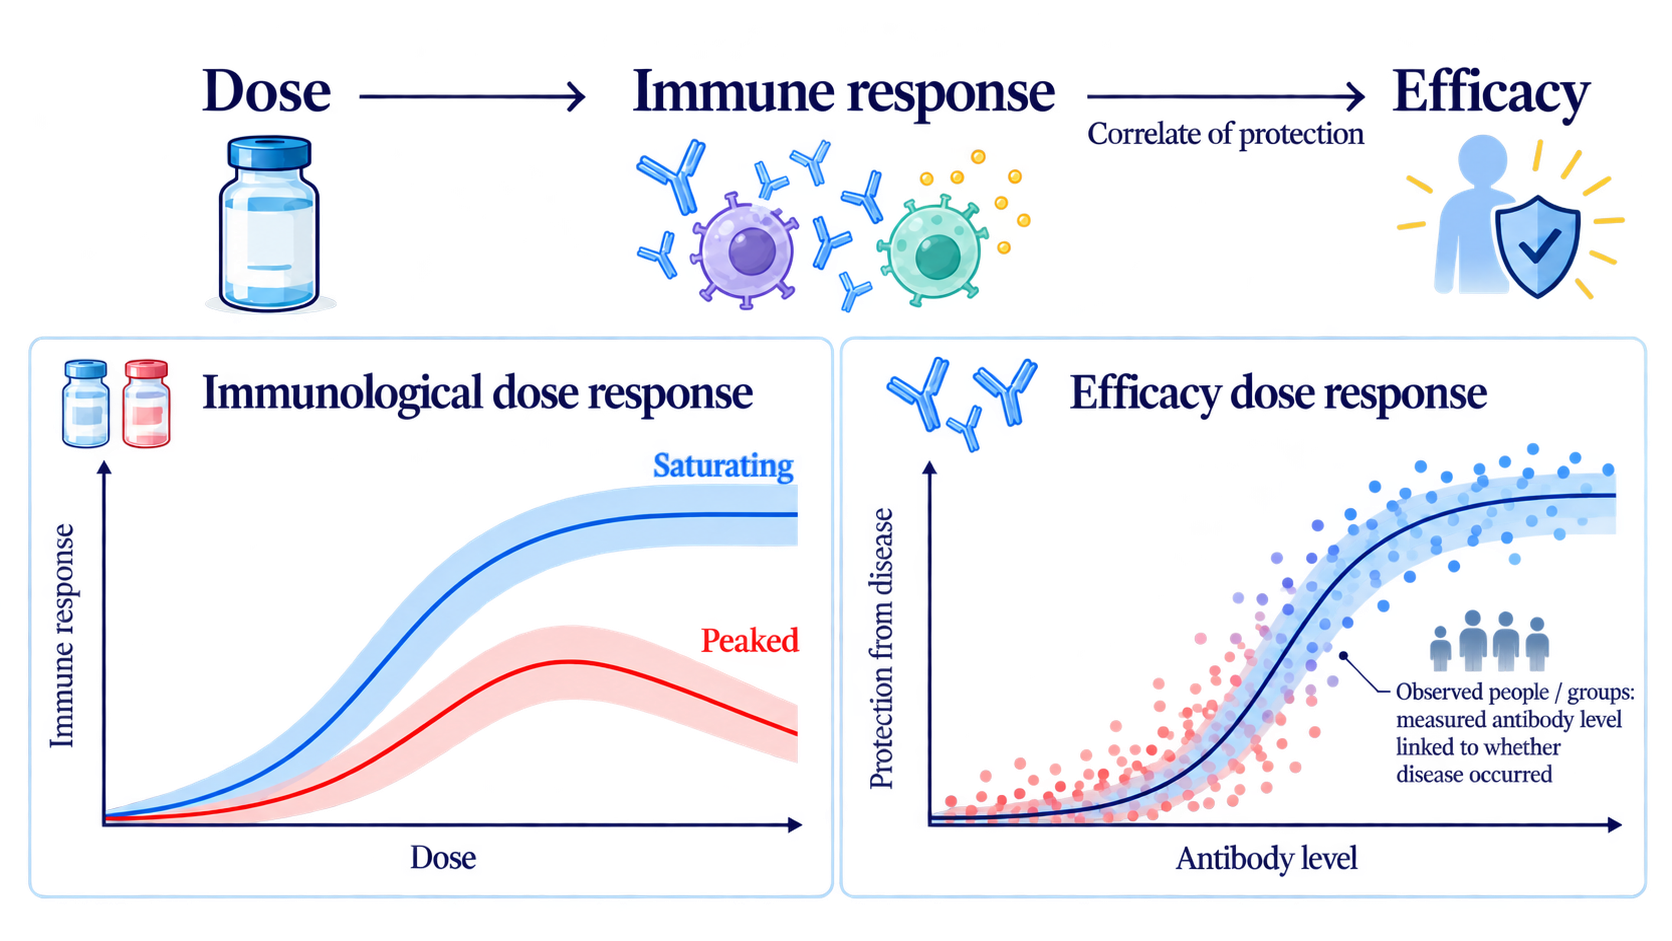
As I suggest on my mock inforgraphic, dose-response curves can take different shapes. Typically we could consider three types:
- concave,
- S-shaped,
- peaked.
Since we are talking about potential benefits from decreasing doses, the most important distinction to us is between peaked and the other two. Must the dose-response curve be non-decreasing in dose? What if past a certain point increasing the dose led to a weaker immune response?4
4 Thinking about dose response as a single 2D curve, like in my examples, is useful for intuitions, but also simplifies things too much. The most important is that we should imagine evolution of the curves over time. For example, imagine two levels of antibodies initially giving 100% efficacy, but only the higher dose giving lifetime protection against disease. Remember as well that we are dealing with statistical relationships. Moreover, the pathogens themselves evolve over time, so we have to consider many curves specific to many different variants. Lastly, there is going to be considerable variability across people, and sometimes also considerable variability in the amount of antigen in a set quantity of vaccine.
Covid example: from dose to immune reponse to efficacy
Let’s see this relationship on an example that will be familiar to us all. Below is a heavily simplified illustration of doses vs antibody responses in early Covid-19 vaccines, where the y axis has been standardised by comparing it to antibody level in people with natural Covid-19 infections.5 It’s hard to compare against vaccines, so in the right panel I normalise the graph so that the dose used in Phase 3 trials has efficacy of 1. I draw a hypothtetical S-shape there, just for illustration.
5 Three publications that are relevant to this mini-example are Khoury et al 2021, Yang et al 2022 and Rhodes et al 2022.
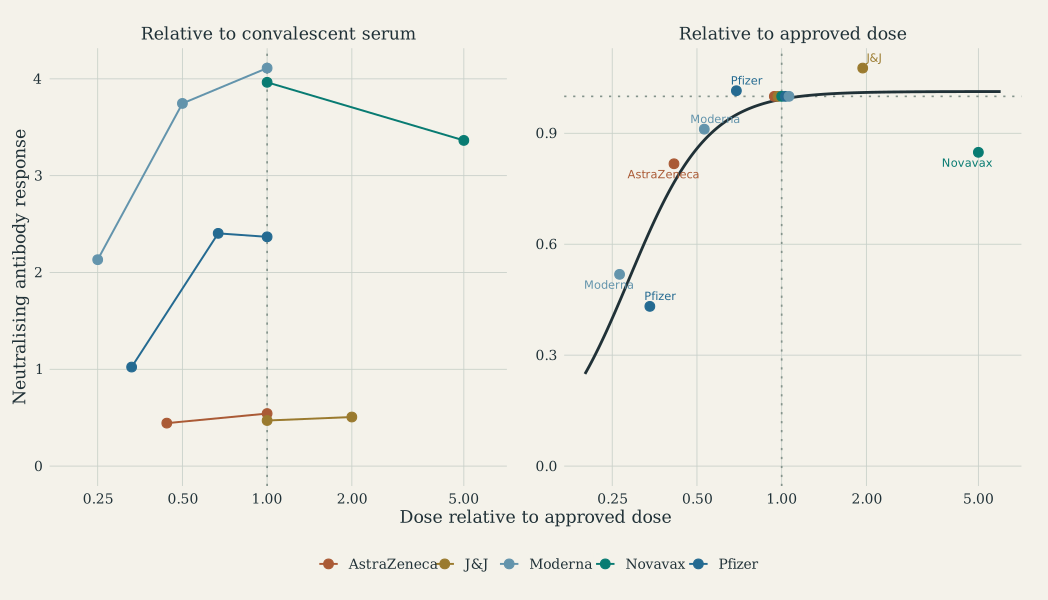
Early in the pandemic researchers understood that neutralising antibodies were a good correlate of protection against Covid. This meant we could use statistical models of the two relationships in my earlier graph: between dose, antibody responses, and efficacy measured in clinical trials. I won’t recap these models here, but here is part of a figure from Yang et al 2022 which I think tells the most relevant part of the story:
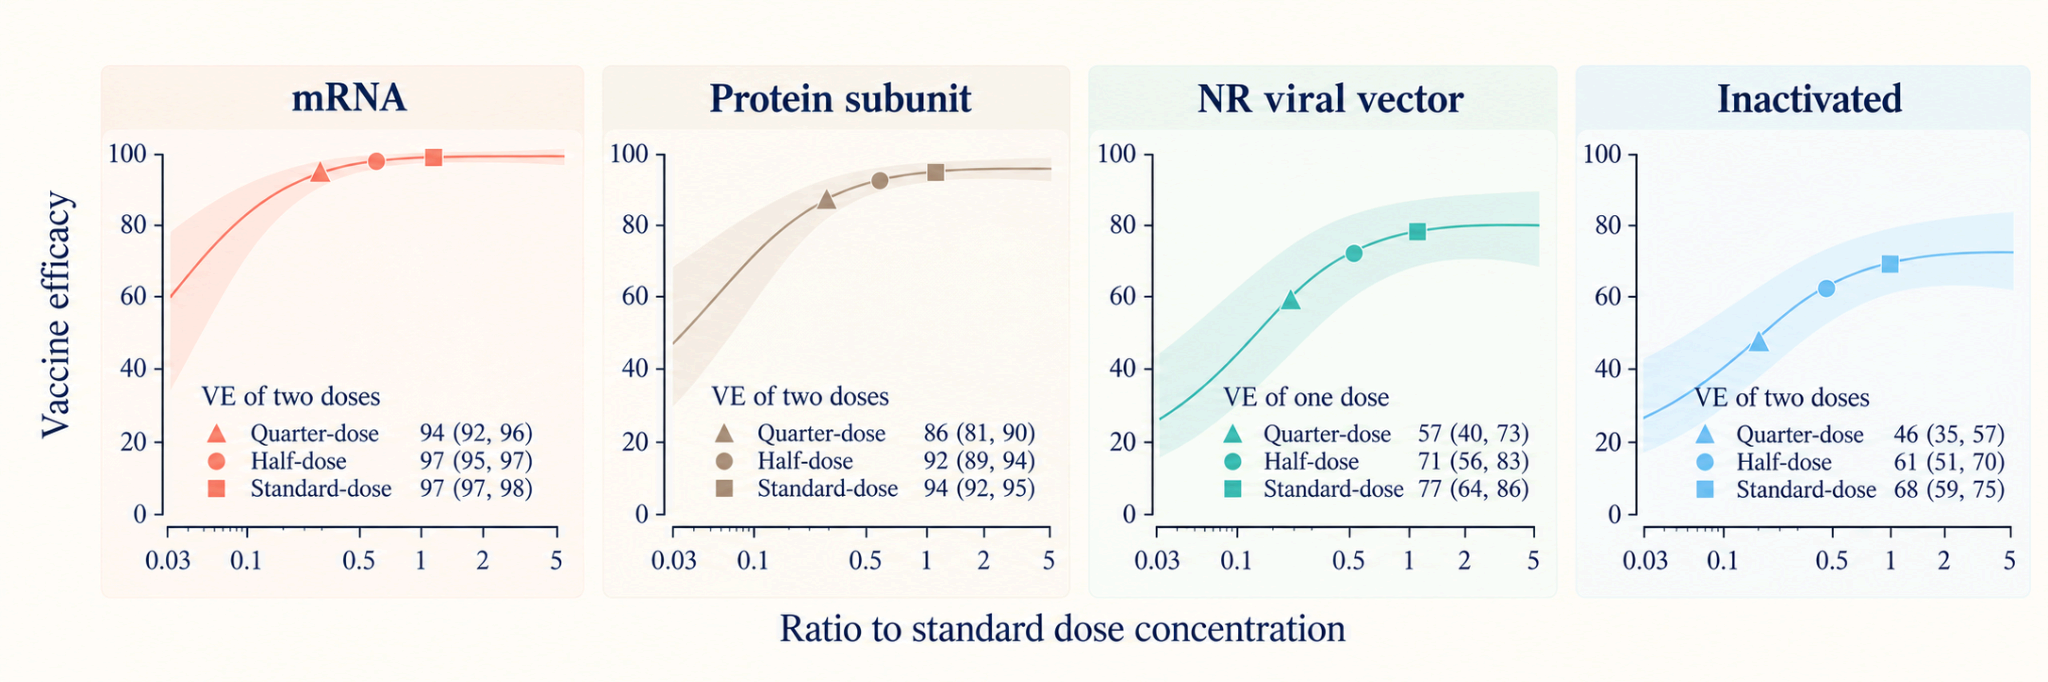
Figure. An illustration of an uncertain, model-derived relationship between dose and efficacy for COVID-19 vaccines.
We see here an example of the general principle that for a given vaccine many doses tested in trials can lie either on “top” of the S or close to it. Remember, however, that these are merely model predictions and that this figure focuses on the magnitude of short-term efficacy, not durability of protection.6
6 Note as well that such a model is for antibody measurements in blood. These are the most useful predictors of protection in this context, but they do not capture mucosal or cellular immunity. So a dose may have high efficacy against symptomatic disease, but low protection against infection or transmission.
Are peaked immune response curves possible?
Earlier I mentioned peaked curves: ones where giving more dose leads to lower immune response. Such a claim may sound counterintuitive but we can find some evidence for it.
- In adenoviral-vector vaccines review by Benest et al (2020) 191 immune-response sets were analysed. Its usually hard to tell saturating and peaked responses apart, but where it is possible, “evidence towards a peaked adenoviral dose-response curve occurred five times more frequently than for a saturating curve”.7
- In Covid-19 Rhodes et al (2022) did similar modeling of 30 immune response datasets and found a mix of peaked and saturating curves.
- In TB vaccines early human trials and animal data, Billeskov et al. (2018), Rhodes et al (2016) and Luabeya et al. (2015) have shown worsening of immune response with higher dose. The first of the three actually showed worsening of protection with higher dose, albeit in mice. This was for candidate vaccines which were discontinued, not for the ones currently in development.
7 Note that the publications I list largely come from the same group of researchers. You may want to discount the evidence slightly for that reason, but I personally think this demonstrates how underexplored the topic of dose-response shapes is.
I think this provides us with enough empirical evidence to at least question whether a higher dose is more effective at preventing disease. But what is the underlying reason for why this may occur? Before we talk about that, let’s say a few things about multi-dose vaccines.
Gaps between doses
Many vaccines require multiple prime and booster doses.8 Continuing with our Covid-19 example, the Astrazeneca vaccine (two-dose) trials measured higher efficacy for patients who were given a lower dose and longer gap between two doses. (The consensus was that it was the gap rather than dose that drove higher efficacy.) This preference for longer gaps could also be seen in antibody response data. In general, many studies of different COVID vaccines have found that longer gaps (without change in dose) between 2 doses (not just of AZ vaccine) led to more robust responses; ditto for third dose.9
8 In the context of the Covid example here, “prime and boost” is used in reference to first and second dose, but it can also refer to priming with two doses and a later 3rd booster dose. Many multi-dose vaccines are given in childhood. In that context “prime” doses would typically be the ones given within the first 6 months of life. A single vaccine can have multiple priming doses (and no booster doses).
9 Of course the trade-off is extending the period where the individuals are protected by only one dose. There are several factors to consider: individual protection, public health perspective from extending protection to more people (“First Doses First”), and risk of mutations. See the section on modeling health benefits of optimal dosing.
Unlike fractionation of a single dose, this mechanism of increased gaps leading to better response was not surprising to experts. Nor is it a mechanism limited to COVID; we will show a few more examples soon. In general terms, when a priming dose of a vaccine is administered, it triggers an initial immune response. Following this, immune responses continue developing over weeks/months. B cells undergo affinity maturation (more on that below) and memory B cells and plasma cells are generated. Following this stimulation of immune system it also enters a refractory period—this is to prevent excessive immune activation and potential harm to the host.
To maximize the benefit of a booster dose, it should be administered after the immune system has generated a pool of memory B and T cells, a period which is highly specific to each vaccine. Consequently, administering a booster dose too early may not elicit a robust secondary response. This also suggests that dosing of boosters will generally differ from dosing of the first dose. We will return to this in a moment.
Possible mechanism: B-cell selection
What follows is definitely beyond my understanding of the immune system and is simply based on rather shallow exploration of existing literature. However, I believe it is fair to say that for many of these mechanisms there is no consensus among immunologists which would be grounded in hard empirical facts. Immunology is not only very difficult, but also many relevant mechanisms elude direct observation, so we have to rely on theory and computer modeling. Treat all of what follows as hypotheticals of varying quality.
Staying with the earlier Covid examples, a modeling study by Garg et al. (2021) suggests a possible explanation for the mechanism observed in the AZ study, which extends beyond delayed booster and also applies to lower doses. It can be most simply summarised as a quantity-quality trade-off that occurs in germinal centers, i.e. the locations where antigens are presented to B cells, which then leads to production of memory B cells and long-lived plasma cells (residing in bone marrow).
In that (generic, i.e. non-Covid-specific) process of affinity maturation, as B cells proliferate, they undergo somatic hypermutation and then clonal selection. This second step is crucial. When there is a lot of antigen, B cells with both moderate and high affinity will bind to it. Hypothetically, when the prime dose is lower, then fewer B cells are selected, but they are on average higher affinity, leading to a stronger immune response (higher quality antibodies) from those cells when antigen is encountered again.10
10 To complicate this further, we should also think about T cell response and its role in immune memory. Expansion and differentiation of B cells into memory B cells, which will then persist and determine quality of future immune response, is promoted by follicular helper T cells (TFH), a type of CD4+ cell. Generally, while stronger T cell responses are observed when activated by a high affinity antigen, the relationship between antigen dose and T cell response is less directly related to strength of response and more related to the types of cells that differentiate, including TFH (Keck et al. 2014). But I do not really understand this mechanism.
The length of this process is measured in (a few) weeks. Going back to the previous subsection, the value of delayed boost can also be explained through what happens in germinal centers. Since the process of selecting cells takes time (proliferate, mutate, be selected), the length of the gap will impact the quality of immune memory.
However, it’s important to note that when such trade-off is cited for a specific vaccine, it is (usually? always?) as a hypothetical mechanism that is backed by simulations and I do not know what weight to put on that hypothesis. I also have no sense of how to generalise from isolated examples to other cases, although there is no reason why it should be seen as COVID-specific. For multi-dose vaccination regimens, it is even less clear what happens to this mechanism, since we do not know whether boosting leads to formation of new germinal centers or modulation of existing ones.11
11 ChatGPT contradicts me here, saying: “Human studies now show that booster vaccination can stimulate new germinal-centre reactions and recruit existing memory B cells into further rounds of maturation. (Alsoussi et al. 2023) What remains uncertain is how antigen dose and timing determine the magnitude, composition and eventual protective value of these responses.”
Before we move on, let me reiterate two points:
- First, these issues are very complex and not only beyond my own understanding, but also not well understood by the experts.
- Second, while I often focus on COVID examples (because they are salient), the mechanisms likely apply in many different diseases.
Immune memory, previous exposure
The main conclusion from the previous section, however, is that we should consider lowering dosage of priming and boosting doses as two separate problems. For priming, the initial response has to be robust enough. For boosting, however, it is generally accepted among practitioners that lower doses may be better. Various vaccine development guidelines acknowledge this; e.g. WHO, pg 35: “If an immune memory response is elicited in the primary series it may be possible to achieve a robust anamnestic response using a much lower dose of an antigenic component compared to the primary series. A lower boosting dose may also provide a better safety profile (for example, as occurs with diphtheria toxoid)”.
The relevant mechanism here is not limited to immunity induced by vaccination. Priming can also come from natural infection. This also means that the effectiveness of vaccines may be highly dependent on history of previous infections, as was the case with COVID-19.12
12 For example, Mateus et al. (2021) found that pre-existing cross reactive T cells enhanced immunogenicity of lower dose of Moderna’s mRNA vaccine. There are many papers on prior infections, e.g. Reynolds et al (2021) and, as I discuss in the chapter on modeling health benefits of optimal dosing, this was translated into models of benefits.
13 Another factor, albeit one that I have not had time to understand yet and just want to name-check topically, has to do with epitope masking. Zarnitysyna et al give both an overview and mathematical models of this mechanism in influenza and difficulty in creating a universal influenza vaccine that could work against the conserved part of the virus.
However, for natural immunity, the factors that determine this are complex and disease-specific. One mechanism is over-stimulation in previously primed individuals. For example, in post-exposure TB vaccination that I mentioned earlier (Billeskov et al. 2018) T cells primed by prior TB exposure were highly susceptible to over-stimulation. The findings there underscore the importance of carefully optimising antigen doses, especially for therapeutic vaccination of previously exposed/primed individuals, in order to induce T cells of optimal functional quality rather than just maximum magnitude. But we can’t generalise this across pathogens, it’s just an example.13
Other ideas: anti-vector immunity, interactions with adjuvants, heterologous boost
There are three more concepts that bear at least mentioning, but which I did not have time to cover under this initial exploration:
Anti-vector immunity: For the COVID-19 AstraZeneca vaccine specifically anti-vector immunity has been hypothesised as the responsible mechanism: that is, immune response to the adenoviral vector which delivers the SARS-CoV 2 antigen may confound the response to COVID antigen. Boosting with viral vector may simply lead to neutralisation of the vector and poor response.14 Currently viral vectors are used for COVID and ebola vaccines only (in development for HIV, malaria).
Heterologous prime-boost (“mix-and-match”) strategies involve the activation of a broader range of immune responses.15 Different vaccine platforms can stimulate distinct aspects of the immune system and mixing can lead to more comprehensive immune response. It also seems to be a good way to avoid anti-vector immunity. However, this is not really in scope of this investigation.
In adjuvanted vaccines, these mechanisms are further complicated by interaction of the vaccine with its adjuvant. Intuitively, given a potent adjuvant, the immune response may be less responsive to changes in dose compared to the same vaccine given without adjuvant. Dosing studies often have to vary both the antigen and the adjuvant. See, for example, dose ranging trials for M72 TB vaccine and its AS01 adjuvant.
14 AstraZeneca vaccine used two doses with the same adenovirus, but the Russian Sputnik V vaccine, also two-dose, used Ad5 and Ad26, presumably to avoid that issue.
15 A lot of COVID vaccine research in 2021 focused on heterologous boosting, with generally positive results for mix-and-match approaches. The best example was the trial in the UK. Nowadays, I think general consensus seems to be that heterologous boosting with a good quality vaccine is a good idea.
Extra example: malaria and RTS,S
Let’s look at another example that shows increasing gaps and smaller doses at the same time can lead to better responses. That is the case in RTS,S and malaria. As nicely summarised in a short editorial by McCall, Yap, and Bousema (2020), the series of the initial three RTS,S doses may work better if the third dose was smaller and delayed by several months. They provide a summary of some possible mechanisms. I am not able to parse it, but it seems that cellular immunity plays a role too in fractionation.16 I should note, however, that it was not clear whether the improved response was due to fractionation, delay, or both (perhaps the consensus has changed since). The affinity maturation explanation may also apply here, but overall it really is a very detailed, complicated, and not well-established mechanism: see the beginning of discussion in (Das et al. 2021).17
16 One of the cited articles, a 2020 paper on RTS,S delayed dose by Pallikkuth et al, references the mechanisms we discussed above right there in the title: A delayed fractionated dose RTS,S AS01 vaccine regimen mediates protection via improved T follicular helper and B cell responses
17 Another interesting topic for further research is the impact of adjuvants on dosing of malaria vaccines (RTS,S, R21) and combination with viral vectors, as in this Nature paper by researchers from Jenner Institute, but this is in mice.
Which vaccines make for good fractionation candidates?
Given the above, can we classify vaccines/diseases according to how lower doses are expected to perform? Clearly the mechanisms that favour lower doses or alternative vaccination regimens are highly variable, depending on platform, pathogen/antigen/epitope complexity, the type of immune machinery that they produce, and history of natural exposures. For COVID, it has been sufficient for vaccines to present a spike protein antigen and neutralising antibodies correlated very well to protection from disease. This meant that some generalisable inferences about impact of lowering doses could be made even early on in the pandemic, as we’ve seen in the initial example in this chapter.
Still, since we’ve been focusing on immune memory, for general interest it may be instructive to delineate three groups of diseases based on that distinction, which I borrow from an excellent summary article by Pollard and Bijker (2021).
| Mechanism | Examples | Hypothetical goal of optimisation approach |
|---|---|---|
| Long-lasting protection. Antibody levels stay high enough to be protective long-term, sometimes lifetime | yellow fever (“only 12 known cases of yellow fever post-vaccination have been identified, after 600 million doses have been dispensed” per WHO), measles-mumps, maybe HPV? | Finding the right dose to induce protection; can involve lowering doses, for vaccines that already tend to work well |
| Memory-dependent protection. Antibody levels drop over time but when exposed, the incubation period is long enough for immune memory to kick in and offer protection | hepatitis B, polio | Optimising for high quality memory, e.g. via timing of doses |
| Short-term antibody-dependent protection. Antibody levels drop rapidly, and the pathogen’s incubation period is too short for memory responses to be fully protective. | influenza, pertussis (acellular), SARS-CoV-2, cholera | Achieving high initial levels of antibodies; public health trade-offs to maximise protection |
Three rather obvious caveats:
- It’s important to note that these categories are not rigid, many vaccines may exhibit characteristics of multiple groups or fall outside these classifications entirely. For example, hepatitis B vaccine requires high levels of antibodies, but is durable; malaria and BCG vaccines have more complicated mechanisms of protection.
- Whether something is “long-lasting” of course depends on context/risk.
- My hypothetical goals are also a bit of splitting hairs. In each case it depends not just on the quality of the vaccine, but also its supply and each disease needs to be considered separately.
However, the point of this simple table is that it’s worth keeping in mind that biological basis for the kind of fractionation that can be done for e.g. yellow fever doesn’t really translate into e.g. pandemic influenza, even though in particular situations we want to optimise doses of both of these. I work through a longlist of diseases closer to the end of this investigation, in summary of optimisation targets.
Role of age (host factors)
In this note, when talking about dose optimisation I generally focused on things that are good ideas on average, i.e. assuming every person gets the same dose or schedule. However, before we conclude, let’s point out the obvious heterogeneity in responses.
We already mentioned previous infection status as an important host factor in vaccine response. Another one is age. It is uncontroversial to give smaller doses of some vaccines to children compared to adults, as their immune systems are generally more responsive. So in children higher doses may lead to increased reactogenicity without any benefits. Conversely (and perhaps more interestingly), for influenza we recommend giving larger doses to the elderly population to overcome immunosenescence and improve vaccine efficacy. Similar schemes could also be considered in diseases with steep increase in risks with age, such as COVID. I return to this idea in the section on modeling health benefits of optimal dosing.
References
Benest, John, Sophie Rhodes, Sara Afrough, Thomas Evans, and Richard White. 2020. “Response Type and Host Species May Be Sufficient to Predict Dose-Response Curve Shape for Adenoviral Vector Vaccines.” Vaccines 8 (2): 155. https://doi.org/10.3390/vaccines8020155.
Billeskov, Rolf, Thomas Lindenstrøm, Joshua Woodworth, Cristina Vilaplana, Pere-Joan Cardona, Joseph P. Cassidy, Rasmus Mortensen, Else Marie Agger, and Peter Andersen. 2018. “High Antigen Dose Is Detrimental to Post-Exposure Vaccine Protection Against Tuberculosis.” Frontiers in Immunology 8 (January): 1973. https://doi.org/10.3389/fimmu.2017.01973.
Das, Jishnu, Jonathan K. Fallon, Timothy C. Yu, Ashlin Michell, Todd J. Suscovich, Caitlyn Linde, Harini Natarajan, et al. 2021. “Delayed Fractional Dosing with RTS,S/AS01 Improves Humoral Immunity to Malaria via a Balance of Polyfunctional NANP6- and Pf16-specific Antibodies.” Med 2 (11): 1269–1286.e9. https://doi.org/10.1016/j.medj.2021.10.003.
Garg, Amar K., Soumya Mittal, Pranesh Padmanabhan, Rajat Desikan, and Narendra M. Dixit. 2021. “Increased B Cell Selection Stringency In Germinal Centers Can Explain Improved COVID-19 Vaccine Efficacies With Low Dose Prime or Delayed Boost.” Frontiers in Immunology 12.
Keck, Simone, Mathias Schmaler, Stefan Ganter, Lena Wyss, Susanne Oberle, Eric S. Huseby, Dietmar Zehn, and Carolyn G. King. 2014. “Antigen Affinity and Antigen Dose Exert Distinct Influences on CD4 T-cell Differentiation.” Proceedings of the National Academy of Sciences of the United States of America 111 (41): 14852–57. https://doi.org/10.1073/pnas.1403271111.
Khoury, David S., Deborah Cromer, Arnold Reynaldi, Timothy E. Schlub, Adam K. Wheatley, Jennifer A. Juno, Kanta Subbarao, Stephen J. Kent, James A. Triccas, and Miles P. Davenport. 2021. “Neutralizing Antibody Levels Are Highly Predictive of Immune Protection from Symptomatic SARS-CoV-2 Infection.” Nature Medicine 27 (7): 1205–11. https://doi.org/10.1038/s41591-021-01377-8.
Luabeya, Angelique Kany Kany, Benjamin M. N. Kagina, Michele D. Tameris, Hennie Geldenhuys, Soren T. Hoff, Zhongkai Shi, Ingrid Kromann, et al. 2015. “First-in-Human Trial of the Post-Exposure Tuberculosis Vaccine H56:IC31 in Mycobacterium tuberculosis Infected and Non-Infected Healthy Adults.” Vaccine 33 (33): 4130–40. https://doi.org/10.1016/j.vaccine.2015.06.051.
Mateus, Jose, Jennifer M. Dan, Zeli Zhang, Carolyn Rydyznski Moderbacher, Marshall Lammers, Benjamin Goodwin, Alessandro Sette, Shane Crotty, and Daniela Weiskopf. 2021. “Low-Dose mRNA-1273 COVID-19 Vaccine Generates Durable Memory Enhanced by Cross-Reactive T Cells.” Science 374 (6566): eabj9853. https://doi.org/10.1126/science.abj9853.
McCall, Matthew B B, Xi Zen Yap, and Teun Bousema. 2020. “Optimizing RTS,S Vaccination Strategies: Give It Your Best Parting Shot.” The Journal of Infectious Diseases 222 (10): 1581–84. https://doi.org/10.1093/infdis/jiaa423.
Pollard, Andrew J., and Else M. Bijker. 2021. “A Guide to Vaccinology: From Basic Principles to New Developments.” Nature Reviews Immunology 21 (2): 83–100. https://doi.org/10.1038/s41577-020-00479-7.
Rhodes, Sophie J., Andrea Zelmer, Gwenan M. Knight, Satria Arief Prabowo, Lisa Stockdale, Thomas G. Evans, Thomas Lindenstrøm, Richard G. White, and Helen Fletcher. 2016. “The TB Vaccine H56+IC31 Dose-Response Curve Is Peaked Not Saturating: Data Generation for New Mathematical Modelling Methods to Inform Vaccine Dose Decisions.” Vaccine 34 (50): 6285–91. https://doi.org/10.1016/j.vaccine.2016.10.060.
Rhodes, Sophie, Neal Smith, Thomas Evans, and Richard White. 2022. “Identifying COVID-19 Optimal Vaccine Dose Using Mathematical Immunostimulation/Immunodynamic Modelling.” Vaccine 40 (49): 7032–41. https://doi.org/10.1016/j.vaccine.2022.10.012.
Sanchez, Sarah, Nicole Palacio, Tanushree Dangi, Thomas Ciucci, and Pablo Penaloza-MacMaster. 2021. “Fractionating a COVID-19 Ad5-vectored Vaccine Improves Virus-Specific Immunity.” Science Immunology 6 (66): eabi8635. https://doi.org/10.1126/sciimmunol.abi8635.
Yang, Bingyi, Xiaotong Huang, Huizhi Gao, Nancy H. Leung, Tim K. Tsang, and Benjamin J. Cowling. 2022. “Immunogenicity, Efficacy, and Safety of SARS-CoV-2 Vaccine Dose Fractionation: A Systematic Review and Meta-Analysis.” BMC Medicine 20 (1): 409. https://doi.org/10.1186/s12916-022-02600-0.
Yang, Zhi-Rong, Yi-Wen Jiang, Fu-Xiao Li, Di Liu, Teng-Fei Lin, Zi-Yi Zhao, Chang Wei, et al. 2023. “Efficacy of SARS-CoV-2 Vaccines and the Dose–Response Relationship with Three Major Antibodies: A Systematic Review and Meta-Analysis of Randomised Controlled Trials.” The Lancet Microbe 4 (4): e236–46. https://doi.org/10.1016/S2666-5247(22)00390-1.